Healthcare & Nursing · New Zealand

Healthcare cares around the clock. Who looks after its sleep?

Nurses and doctors work rotating 24/7 rosters, nights and extended shifts. Fatigue impairs attention and judgement, putting medication safety, clinical decisions and the drive home at risk.

Regulation changed 9 Jul 2026Change coming 1 Apr 2027

Healthcare & Nursing workforce

Who this page covers

  • After-hours GP and home-visit doctors
  • Doctors in training (residents)
  • Forensic mental health hospitals (also see Corrections & Custodial Services)
  • Hospital pathology and imaging
  • Nursing agencies and locum pools (also see Professional Services)
  • Private hospitals
  • Psychiatric hospitals and inpatient mental health
  • Public hospitals

Reg Watch

What’s changed, and what’s coming

Regulatory change that affects how you manage fatigue in healthcare & nursing: what has changed in the last 12 months, and what is on the way.

Recent changeFrom 9 July 2026

Applies across industries in New Zealand

The Health and Safety at Work Amendment Act 2026 became law on 9 July 2026. Your duties do not change until most of it commences on 1 April 2027, so use the lead time to evidence fatigue as a serious-harm risk.

Read the change

Upcoming changeExpected from 1 April 2027Within 12 months

From 1 April 2027 HSWA centres on 'critical risks'. Fatigue is not on the Schedule 1A list, so it counts only where it is likely to cause death or notifiable harm. Firms under 20 workers manage critical risks only; following an approved code is deemed compliance; officer duties become governance-level.

Regulatory changes checked as at 1 October 2026.

Regulation

Who regulates it, and what they expect

No New Zealand statute caps how long a nurse or doctor can work. The binding limits sit in the collective agreements Health New Zealand signs with the resident doctors' unions: a general ceiling of 12 consecutive days on duty or on call before a 48-hour break, tightened to 10 consecutive days and no more than 4 consecutive nights on designated acute rosters, 5 consecutive days in emergency and intensive care, a 16-hour maximum duty and at least 8 hours off between duties. Nursing has a national safe-staffing methodology written into agreements rather than into law, and there is no legislated nurse-to-patient ratio.

Regulated by
  • WorkSafe New ZealandWorkSafe

Logos identify the regulator and don’t imply endorsement.

Who regulates it

Healthcare has a real industry layer above the general regulators. Health New Zealand negotiates roster and hours rules for resident doctors with two unions, the Resident Doctors' Association and Specialty Trainees of New Zealand. A national nurse-staffing methodology, Care Capacity Demand Management, sits in nursing agreements and runs through the Safe Staffing Healthy Workplaces Unit. WorkSafe enforces the duty underneath.

Your obligations

If you employ resident medical officers under either national agreement, you must roster inside firm numbers: no more than 12 consecutive days on duty or on call before a 48-hour rest period, no more than 10 consecutive days and 4 consecutive nights on designated acute rosters, no more than 5 consecutive days in emergency and intensive care, a maximum 16-hour duty and at least 8 hours off between duties. Nursing agreements commit you to the national safe-staffing methodology. Every health employer, inside those agreements or outside them, must also eliminate or minimise fatigue risk so far as is reasonably practicable.

Consequences

Breaking a roster limit or a safe-staffing commitment is an employment matter first. The union or the affected doctor or nurse can take it to the Employment Relations Authority, which can award compensation, impose penalties and order the rostering practice fixed; nurses have also struck lawfully on health and safety grounds and the Employment Court declined to stop them. Separately, if tired rostering contributes to a patient or a staff member being harmed, WorkSafe can prosecute under the Health and Safety at Work Act 2015 whether or not an agreement was breached, and a written limit your own rosters ignored is powerful evidence the risk was foreseeable and that you could reasonably have managed it.

Penalties

Under the Health and Safety at Work Act 2015 an organisation faces up to $3m for reckless exposure to death or serious injury, $1.5m where the exposure is not reckless and $500,000 for a duty breach. A director or senior manager faces $600,000, $300,000 or $100,000, plus up to five years' imprisonment at the top tier. These are the 2015 amounts, still in force in 2026 and not indexed. Reparation to the victim is assessed first and added on top of the fine.

Sources: NZ Resident Doctors' Association rostering rules and Safer Rosters campaign; Health New Zealand collective agreements with NZRDA and STONZ; Health and Safety at Work Act 2015 and WorkSafe penalty guidance; Ministry of Health review of Care Capacity Demand Management.

Fatigue-critical roles

Where fatigue matters most in healthcare & nursing

The roles where a fatigued worker is most likely to cause serious harm, the tasks that carry the risk, and why fatigue builds up in them.

RoleRiskHigh-risk tasksWhy fatigue builds
Resident medical officer (RMO): house officer (PGY1-2), registrar
Rules
Regulatory designation
None specific - general duty (HSWA 2015 s 36); RMO limits are contractual (Health NZ/NZRDA and STONZ collective agreements)
Hours and rest
No statutory cap. NZRDA CA: max 16 h duty/day, min 8 h between duties, max 12 consecutive days; Sch 10 acute rosters max 4 consecutive nights; STONZ cl 17: max 72 h in 7 days
Critical riskPrescribing and dosing, procedures and admitting unwell patients alone overnight; handover after a night shift or 24 h on-call; driving home afterwardsRotating nights, 12-14 h long days, 24 h on-call in some systems, quick returns; 60-80 h weeks in training posts
Registered nurse (RN) / registered midwife; enrolled nurse (EN)
Rules
Regulatory designation
None specific - general duty (HSWA 2015 s 36); roster terms in Health NZ/NZNO collective agreement (contract, not law)
Hours and rest
No statutory maximum; NZNO CA cl 6 roster design to minimise fatigue (contract); ERA 2000 Part 6D breaks
Critical riskHigh-alert medicines (insulin, opioids, IV infusions) and double-checks at 03:00-05:00; observing deteriorating patients; patient handling; driving home after nights12 h day/night rotations or rotating 8/10 h shifts, quick returns, mandatory or voluntary overtime, consecutive nights
Senior medical officer (SMO) / specialist
Rules
Regulatory designation
None specific - general duty (HSWA 2015 s 36; fatigue named in s 16 'hazard')
Hours and rest
No statutory maximum; Health NZ/ASMS SMO collective agreement on-call terms (contract)
Critical riskEmergency surgery, anaesthesia and obstetric delivery at night after a full day list; next-day elective list after being called in; driving in at 03:00Non-resident on-call 1:3 to 1:8, called in overnight, then a full day list next day; no rest rule after call-ins in most systems
Healthcare assistant (HCA) / hospital aide
Rules
Regulatory designation
None specific - general duty (HSWA 2015 s 36; fatigue named in s 16 'hazard')
Hours and rest
No statutory maximum; ERA 2000 Part 6D rest and meal breaks
High riskTwo-person patient transfers and repositioning, overnight falls watch and 1:1 observation ('specialling'), vital-sign rounds and escalation, mobilising patientsRotating or permanent nights, 12 h shifts, bank/agency shifts stacked on a primary job, 07:00 handovers
Hospital pharmacist
Rules
Regulatory designation
None specific - general duty (HSWA 2015 s 36; fatigue named in s 16 'hazard')
Hours and rest
No statutory maximum; ERA 2000 Part 6D rest and meal breaks
High riskVerifying and dispensing high-alert and paediatric doses overnight, aseptic compounding checks (chemotherapy, TPN), phone advice to wards while alone on-callResident nights in large hospitals or remote on-call after a day shift; lone overnight verification with no second checker
Medical laboratory scientist / medical imaging technologist (MIT)
Rules
Regulatory designation
None specific - general duty (HSWA 2015 s 36; fatigue named in s 16 'hazard')
Hours and rest
No statutory maximum; ERA 2000 Part 6D rest and meal breaks
High riskCross-matching and issuing blood, phoning critical results, CT and X-ray imaging and contrast checks overnight; lone on-call after a day shiftSingle-handed nights or call-ins after a full day, 24 h weekend on-call, broken sleep between call-ins

Stories

When fatigue made the record

Published findings and prosecutions from regulators, courts and investigators in New Zealand.

  • Jan 2025 · Auckland, New Zealand

    Night-shift recovery support worker filmed sleeping wins unjustified dismissal case after employer tolerated sleeping

    • Legal
    • Financial

    A long-serving recovery support worker who worked 12-hour night shifts alone at a 24-hour residential service for high-needs residents, run by a community trust, was secretly filmed sleeping for up to about three hours a shift and summarily dismissed. The Employment Relations Authority found night staff had a legitimate expectation, from a 2021 meeting, that they could sleep during a combined two-and-a-half-hour break (though no contractual entitlement), that management had turned a blind eye to sleeping, and that the trust had cut 16-hour shifts to 12 hours partly because staff could nod off. The dismissal was unjustified; reinstatement was declined and remedies were reduced 25% for contribution.

    Case NZ-healthcare-04Report an issue

See all healthcare & nursing news

How the suite fits

How each product connects to your obligations

Grades describe how strongly a product connects to an obligation. None discharges an obligation, and none carries a compliance warranty.

Sleepfit

Supports your general duty of care

No New Zealand law names a sleep screen for clinicians; Health NZ's collective agreements address rosters, not screening. Your s 36(3)(g) duty to monitor worker health applies, and Sleepfit supports it. It screens; diagnosis stays with your clinicians.

About Sleepfit

Fatiguefit4Duty

Supports your general duty of care

No New Zealand law sets a pre-duty fatigue check for clinicians. Health NZ's resident doctor agreement commits it to fatigue mitigation; your s 36 duty applies across the sector. A fitness-for-duty check, not a fitness-for-duty decision - the duty call stays with you.

About Fatiguefit4Duty

Awareness eLearning

Supports your general duty of care

At Health NZ, the resident doctors' collective agreement commits RMOs to take part in fatigue mitigation programmes; elsewhere your s 36(3)(f) training duty applies. Awareness eLearning supplies fatigue and sleep content.

About Awareness eLearning

Was It Fatigue?

Supports your general duty of care

No New Zealand health rule requires you to assess fatigue after an adverse or notifiable event; s 56 of the Health and Safety at Work Act 2015 requires notification without naming a cause. A structured judgement aid, not a determination of cause.

About Was It Fatigue?

SleepWellBaby

No New Zealand health sector rule reaches sleep in new-parent households. SleepWellBaby is offered to parents of infants in your workforce as a benefit that protects their own sleep, not as a compliance step.

About SleepWellBaby

Recommended bundle

Where we’d start in healthcare & nursing

Every bundle is priced on prevalence: your whole cohort gets access, and you pay for the share predicted to need each product. How pricing works.

Why this pairing in New Zealand

No health rule names a fatigue tool; HSWA 2015 s 36 applies, and Health NZ's resident doctor agreement commits to fatigue mitigation. Sleepfit screens clinicians, Fatiguefit4Duty adds a pre-duty check, Awareness eLearning trains. Fatigue Lifecycle adds adverse event review.

See what sleep and fatigue mean for your healthcare & nursing workforce.

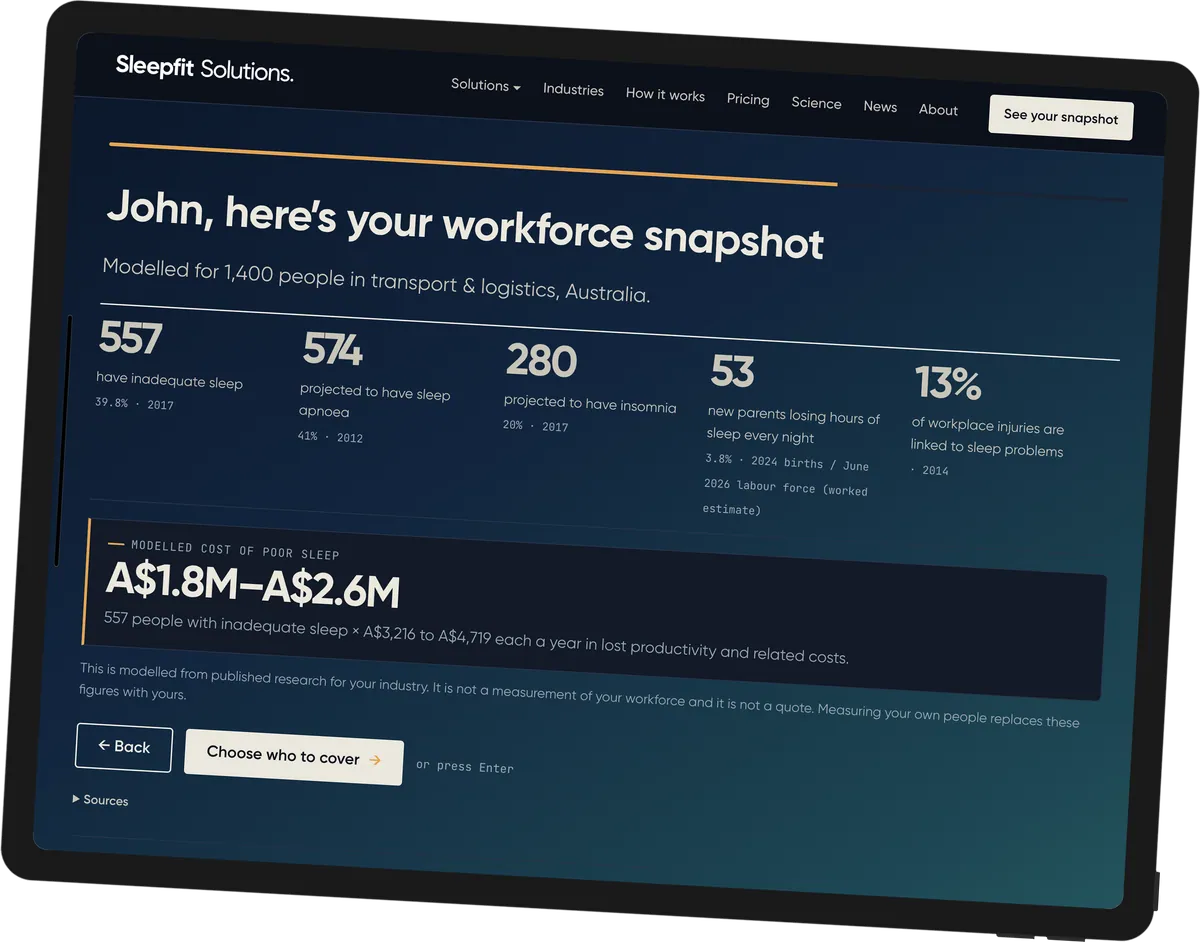
Tell us roughly how many people you employ. Your snapshot models how many are likely sleeping poorly and what it costs, from published research for healthcare & nursing. Then choose who you’d cover, and we’ll take you to the right next step.

A sample workforce snapshot on a tablet: modelled sleep problems and the cost of poor sleep for 1,400 people in transport and logistics.