Healthcare & Nursing · United States

Healthcare cares around the clock. Who looks after its sleep?

Nurses and doctors work rotating 24/7 rosters, nights and extended shifts. Fatigue impairs attention and judgment, putting medication safety, clinical decisions and the drive home at risk.

Healthcare & Nursing workforce

Who this page covers

  • After-hours GP and home-visit doctors
  • Doctors in training (residents)
  • Forensic mental health hospitals (also see Corrections & Custodial Services)
  • Hospital pathology and imaging
  • Nursing agencies and locum pools (also see Professional Services)
  • Private hospitals
  • Psychiatric hospitals and inpatient mental health
  • Public hospitals

Reg Watch

What’s changed, and what’s coming

Regulatory change that affects how you manage fatigue in healthcare & nursing: what has changed in the last 12 months, and what is on the way.

Upcoming changeNo date set yet

Michigan Senate Bills 296 and 297, passed by the Senate on 15 April 2026, would bar mandatory nurse overtime and require 8 hours off after a 12-hour shift; they await the House. Pennsylvania's Patient Safety Act (HB 106) on nurse ratios remains before the Senate.

Regulatory changes checked as at October 1, 2026.

Regulation

Who regulates it, and what they expect

No federal law caps clinical work hours in a US hospital. What binds you is state law and accreditation. Sixteen states restrict mandatory overtime for nurses or for health care employees more broadly, each by a different mechanism, and California, Massachusetts and Oregon set nurse-to-patient ratios. Resident and fellow hours are set by ACGME accreditation standards that bind accredited programs and their sponsoring institutions, not attending physicians and not nurses. New York goes further and makes trainee hours a matter of state regulation for every Article 28 hospital.

Regulated by
  • Centers for Medicare & Medicaid ServicesCMS

Logos identify the regulator and don’t imply endorsement.

Who regulates it

State legislatures and health departments set the binding rules - California, Oregon, New York and Pennsylvania have the strongest. The federal Centers for Medicare and Medicaid Services sets the hospital Conditions of Participation, The Joint Commission accredits most hospitals for Medicare purposes, and the ACGME governs resident physician hours. OSHA, the ADA and the FMLA apply underneath all of it.

Your obligations

If you sponsor an accredited residency or fellowship, work must average no more than 80 hours a week over four weeks, scheduled clinical work periods must not exceed 24 continuous hours plus up to four for handover and teaching, and trainees must have one day in seven free and 14 hours free after 24 hours of in-house call. Eight hours off between work periods is an expectation, not a requirement. In New York the 80-hour average, the 24-hour ceiling and eight non-working hours between assignments are state regulation. Nurse overtime and ratio duties depend entirely on the state.

Consequences

State enforcement is direct. New York's labor department fines mandatory-overtime breaches, Pennsylvania's issues administrative fines, Oregon can impose civil penalties and act against a hospital license, and California ratio breaches draw health-department citations. New York hospitals also answer to the health department for trainee hour breaches under their Article 28 license. A program that breaches the work-hour standards risks ACGME citation or loss of accreditation, which ends it. Federal safety-duty exposure and workers' compensation apply to every fatigue-linked injury.

Penalties

New York: $1,000 first violation, $2,000 second within 12 months, $3,000 third or later, plus up to $500 for reporting breaches. Pennsylvania: $100 to $1,000 per violation. Oregon: civil penalties for conduct on or after 1 June 2025. OSHA general duty: $16,550 serious, $165,514 wilful or repeat (2025 levels, in force for 2026).

Sources: Cal. Code Regs. tit. 22 s70217 and IWC Wage Order 5; Oregon ORS 441.762-441.792, OAR 333-510-0130; NY Labor Law s167; Pennsylvania Act 102 of 2008; ACGME Common Program Requirements Section VI; Joint Commission National Performance Goal 12; 42 CFR 482.23; OSHA 2026 penalty schedule.

Fatigue-critical roles

Where fatigue matters most in healthcare & nursing

The roles where a fatigued worker is most likely to cause serious harm, the tasks that carry the risk, and why fatigue builds up in them.

RoleRiskHigh-risk tasksWhy fatigue builds
Resident physician (PGY-1 intern, resident, fellow)
Rules
Regulatory designation
Resident in an ACGME-accredited program (duty hours are accreditation standards, not law); in New York a 'postgraduate trainee' under 10 NYCRR 405.4(b)(6) (state regulation)
Hours and rest
ACGME CPR VI: 80 h/wk averaged over 4 wks, 24 h + 4 h transition, 1 day in 7 free. NY 405.4(b)(6): avg 80 h/wk over 4 wks, max 24 consecutive scheduled h, 8 h off between duties
Critical riskPrescribing and dosing, procedures and admitting unwell patients alone overnight; handover after a night shift or 24 h on-call; driving home afterwardsRotating nights, 12-14 h long days, 24 h on-call in some systems, quick returns; 60-80 h weeks in training posts
Registered nurse (RN), staff nurse; licensed practical/vocational nurse (LPN/LVN)
Rules
Regulatory designation
None specific - general duty; state mandatory-overtime restrictions in about 16 states (e.g. NY Labor Law s 167; PA Act 102 of 2008)
Hours and rest
No federal cap. e.g. Or. OAR 333-510-0130: max 12 h in 24 and 48 h/wk, 10 h rest after a 12th hour; Cal. Wage Order 5 s 3: no required >12 h in 24 on 12 h AWS, 16 h hard limit
Critical riskHigh-alert medicines (insulin, opioids, IV infusions) and double-checks at 03:00-05:00; observing deteriorating patients; patient handling; driving home after nights12 h day/night rotations or rotating 8/10 h shifts, quick returns, mandatory or voluntary overtime, consecutive nights
Attending physician (anesthesiologist, surgeon, OB/GYN, hospitalist)
Rules
Regulatory designation
None specific - general duty; attendings are outside ACGME duty-hour limits
Hours and rest
None - no duty-hour rule for attending physicians
Critical riskEmergency surgery, anaesthesia and obstetric delivery at night after a full day list; next-day elective list after being called in; driving in at 03:00Non-resident on-call 1:3 to 1:8, called in overnight, then a full day list next day; no rest rule after call-ins in most systems
Certified nursing assistant (CNA) / patient care technician (PCT)
Rules
Regulatory designation
None specific - general duty; state mandatory-overtime laws reach CNAs in some states
Hours and rest
No federal hours cap for adults; FLSA prices overtime only
High riskTwo-person patient transfers and repositioning, overnight falls watch and 1:1 observation ('specialling'), vital-sign rounds and escalation, mobilising patientsRotating or permanent nights, 12 h shifts, bank/agency shifts stacked on a primary job, 07:00 handovers
Clinical / staff pharmacist (overnight pharmacist)
Rules
Regulatory designation
None specific - general duty (OSH Act s 5(a)(1); public employers only in State Plan states)
Hours and rest
No federal hours cap for adults; FLSA prices overtime only
High riskVerifying and dispensing high-alert and paediatric doses overnight, aseptic compounding checks (chemotherapy, TPN), phone advice to wards while alone on-callResident nights in large hospitals or remote on-call after a day shift; lone overnight verification with no second checker
Medical laboratory scientist (MLS) / radiologic technologist (RT)
Rules
Regulatory designation
None specific - general duty (OSH Act s 5(a)(1); public employers only in State Plan states)
Hours and rest
No federal hours cap for adults; FLSA prices overtime only
High riskCross-matching and issuing blood, phoning critical results, CT and X-ray imaging and contrast checks overnight; lone on-call after a day shiftSingle-handed nights or call-ins after a full day, 24 h weekend on-call, broken sleep between call-ins

Stories

When fatigue made the record

Published findings and prosecutions from regulators, courts and investigators in the United States.

  • May 2021 · Washington, United States

    Surgical resident with shift work sleep disorder oversleeps after 37 hours' work in two days and is dismissed; accommodation claim fails because he bypassed the disability office

    • Legal

    A second-year orthopaedic surgery resident at a state university in Washington, treated for shift work sleep disorder, had repeated lateness and later testified that sleep deprivation from the disorder caused it. On a trauma rotation at a teaching hospital he overslept and missed rounds after working 37 hours over the previous two days, six days after emailing his program director a first draft of proposed accommodations. The faculty competency committee, told he was failing the rotation even without that day, recommended non-renewal, and the Washington Court of Appeals upheld summary judgment for the university: the accommodation claim failed because he chose to bypass the university's disability services process, and the discrimination and retaliation claims failed because he could not show the performance reasons were a pretext.

    Case US-healthcare-18Report an issue

Story 1 of 20

See all healthcare & nursing news

How the suite fits

How each product connects to your obligations

Grades describe how strongly a product connects to an obligation. None discharges an obligation, and none carries a compliance warranty.

Sleepfit

Supports your general duty of care

Screening your nursing and medical workforce for undiagnosed sleep apnea, insomnia and distress supports your general safety duty. No US healthcare rule requires it, so it is a control you choose.

About Sleepfit

Fatiguefit4Duty

Supports your general duty of care

In an accredited residency or fellowship, a structured fatigue check at the point of work supports the requirement that faculty monitor trainees for signs of excessive fatigue. Elsewhere nothing requires it.

About Fatiguefit4Duty

Awareness eLearning

Supports your general duty of care

No US rule requires fatigue training for hospital staff; Joint Commission Sentinel Event Alert 48 advises it, and ACGME requires fatigue education in accredited residencies. Awareness eLearning supplies that content with a completion record.

About Awareness eLearning

Was It Fatigue?

Supports your general duty of care

No US rule requires fatigue to be examined after an adverse event; Joint Commission Sentinel Event Alert 48 advises it. Was It Fatigue? supports your event review with a structured analysis. A structured judgment aid, not a determination of cause.

About Was It Fatigue?

SleepWellBaby

Supporting new-parent staff through infant sleep is a retention and wellbeing measure for a shift-working workforce. No US healthcare regulation engages it, so it is a benefit, not a safety control.

About SleepWellBaby

Recommended bundle

Where we’d start in healthcare & nursing

Every bundle is priced on prevalence: your whole cohort gets access, and you pay for the share predicted to need each product. How pricing works.

Why this pairing in the United States

No US healthcare rule names a fatigue tool; Joint Commission Sentinel Event Alert 48 advises action, and ACGME requires fatigue education in residencies. Sleepfit screens, Awareness eLearning trains with a record, Fatiguefit4Duty supports trainee monitoring. Fatigue Lifecycle adds event review.

See what sleep and fatigue mean for your healthcare & nursing workforce.

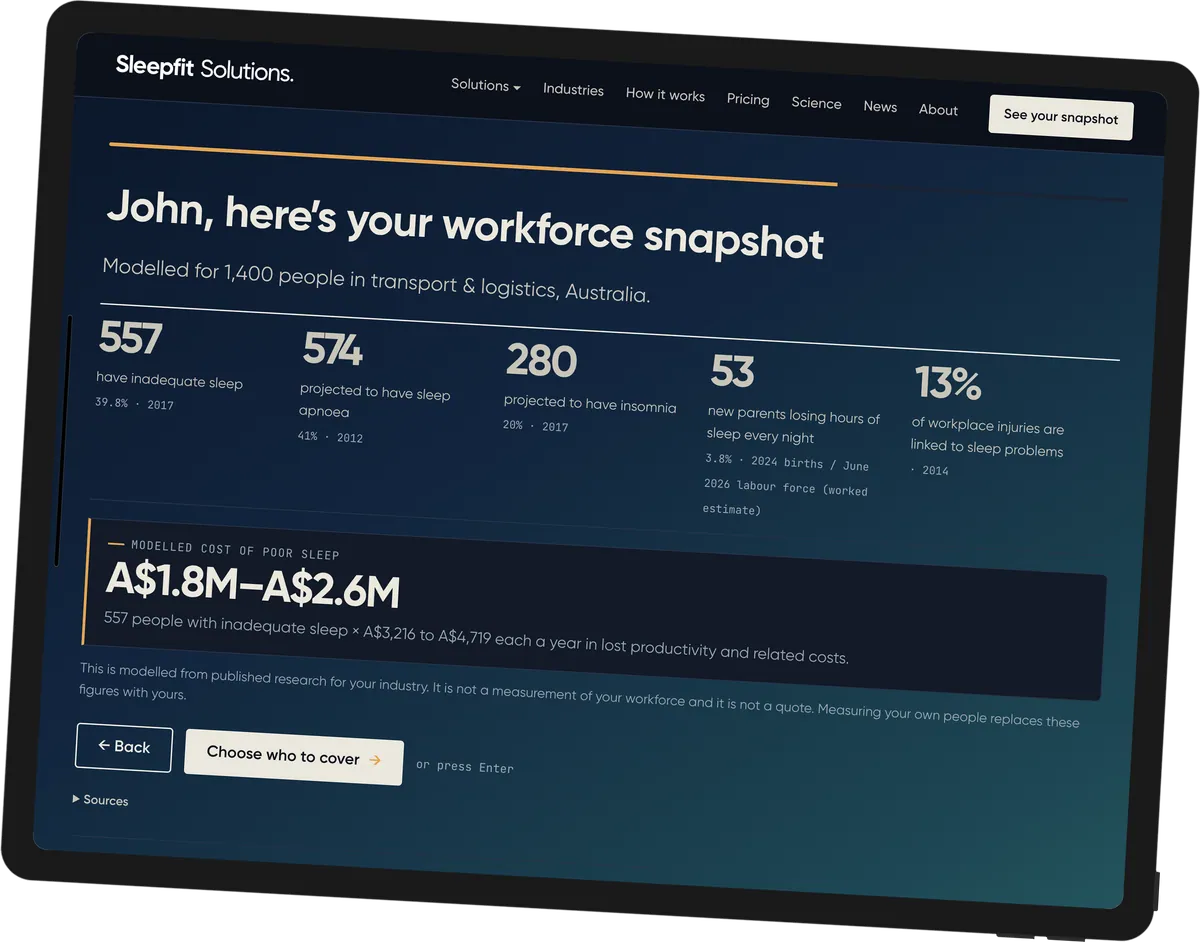
Tell us roughly how many people you employ. Your snapshot models how many are likely sleeping poorly and what it costs, from published research for healthcare & nursing. Then choose who you’d cover, and we’ll take you to the right next step.

A sample workforce snapshot on a tablet: modeled sleep problems and the cost of poor sleep for 1,400 people in transport and logistics.