Supporting other people’s health starts with your own sleep.
Mostly daytime clinic work with heavy caseloads and emotional load; after-hours and crisis on-call add broken sleep. Poor sleep feeds burnout and turnover more than acute safety risk.
Regulatory change that affects how you manage fatigue in mental health & allied health: what has changed in the last 12 months, and what is on the way.
Recent changeFrom 6 April 2026
Applies across industries in the United Kingdom
In Great Britain, from 6 Apr 2026 sick pay is due from the first day of sickness and you must keep holiday records for 6 years; from 1 Oct 2026 most tribunal claims can be brought up to 6 months after the event.
Upcoming changeExpected from 30 October 2026Within 12 months
From October 2026 (expected 30 Oct) you must take all reasonable steps to prevent sexual harassment of staff, including by customers and other third parties. From 1 Jan 2027 unfair dismissal protection starts after 6 months' service. Guaranteed hours and shift-notice rights for zero-hours workers are listed for 2027, timing to follow consultation.
Regulatory changes checked as at 1 October 2026.
Regulation
Who regulates it, and what they expect
Resident doctors work under a national contract with hard rota limits - 72 hours of actual work in any 168 consecutive hours, a 13-hour maximum shift, no more than four consecutive long shifts or four nights, and 11 hours' rest between shifts - policed by exception reporting and a Guardian of Safe Working Hours who fines the department for breaches. Allied health professionals - physiotherapists, occupational therapists, paramedics, radiographers - have no equivalent regime: for them the 48-hour average, daily and weekly rest, breaks and night-worker protections are all there is.
Regulated by
HSE
Logos identify the regulator and don’t imply endorsement.
Who regulates it
NHS 'allied health' splits into two groups: resident (junior) doctors, on their own national contract with real safety mechanisms including a local 'Guardian of Safe Working Hours' empowered to fine the hospital for unsafe rotas; and Allied Health Professionals proper - physios, occupational therapists, paramedics, radiographers - on general NHS terms, governed by the same regulator and tribunal system as any UK worker.
Your obligations
For resident doctors you must roster within contractual limits: 72 hours of actual work in any 168 consecutive hours, no shift over 13 hours, no more than four consecutive long shifts or four consecutive nights, 11 hours' rest between shifts, and a 48-hour weekly average which a doctor may opt out of only up to an average of 56 hours. You must also run exception reporting and appoint a Guardian of Safe Working Hours. For allied health professionals the general position applies: the 48-hour average with the ordinary opt-out, daily and weekly rest, rest breaks, and night-worker limits and health assessments, which matter most for paramedics.
Consequences
For doctors, an unsafe rota carries a direct price: the doctor is paid for the additional hours at penalty rates and the Guardian levies a fine on the department that rostered them, ring-fenced for trainees rather than paid to the state. For allied health professionals the consequences are the ordinary ones. NHS trusts lost Crown immunity in 1991, so HSE can prosecute a trust outright for a fatigue-related safety failure, with an unlimited fine. Staff can bring employment tribunal claims over rest and hours, and anyone harmed where tiredness contributed can sue in negligence.
Penalties
Guardian fines are set per hour of breach by the annual NHS medical and dental pay circular and levied on the department that rostered the doctor; uniquely, the money is not paid to the state but must be spent on trainees. A fatigue-related safety prosecution is sentenced under the guideline in force since 1 February 2016, which scales fines to turnover and leaves them unlimited in the Crown Court, with up to two years' imprisonment for individuals.
On the record
No UK court, coroner, investigator or regulator has published a finding linking fatigue to an incident in allied health. The duty to manage fatigue still sits within the general duties of the Health and Safety at Work etc. Act 1974.
Sources: NHS doctors and dentists in training terms and conditions (England) 2016, version 14, June 2026; NHS terms and conditions of service handbook (Agenda for Change); Working Time Regulations 1998; Health and Safety at Work etc. Act 1974; Health and Care Professions Council.
Fatigue-critical roles
Where fatigue matters most in mental health & allied health
The roles where a fatigued worker is most likely to cause serious harm, the tasks that carry the risk, and why fatigue builds up in them.
Role
Risk
High-risk tasks
Why fatigue builds
Mental health nurse (RMN)Rules
Regulatory designation
Night worker (WTR 1998 reg 2: 3+ h of daily work in night time as a normal course) - free health assessment, reg 7; use of force recorded under the Mental Health Units (Use of Force) Act 2018
Hours and rest
WTR 1998: hospital/residential care is a special case (reg 21(c)) - night limit and daily rest give way to compensatory rest (reg 24); reg 7 assessment still applies; 48 h avg (opt-out)
Critical risk
Constant and intermittent observation of high-risk patients overnight, restraint and seclusion, rapid tranquillisation, ward environment safety checks, absconding watch
Rotating nights and 12 h shifts on acute inpatient units, frequent overtime to cover 1:1 observations
Approved mental health professional (AMHP) / crisis resolution and home treatment practitionerRules
Regulatory designation
AMHP (Mental Health Act 1983 s 114); otherwise general duty
Hours and rest
WTR 1998: 48 h avg (opt-out allowed), 11 h daily rest (reg 10), 20 min break over 6 h (reg 12)
High risk
After-hours Mental Health Act assessments in homes and EDs, detention and risk decisions, driving alone to call-outs at night, de-escalation
Evening and overnight on-call after a day caseload, lone call-outs, long drives in rural areas
Night worker (WTR 1998 reg 2: 3+ h of daily work in night time as a normal course) - free health assessment, reg 7 if employed on nights; volunteers sit outside WTR
Hours and rest
WTR 1998: night work avg 8 h in 24 (reg 6); 48 h avg (opt-out allowed); 11 h daily rest (reg 10)
High risk
Overnight crisis risk assessment on calls and texts, deciding on emergency dispatch, safety planning, sustained vigilance through long quiet periods
Overnight shifts (often 23:00-07:00), volunteer shifts after a day job, remote work from home at night
Community physiotherapist / OT (rural NHS trust or health board)Rules
Regulatory designation
None specific - general duty (HSWA 1974 s 2; MHSWR 1999 reg 3)
Hours and rest
WTR 1998: 48 h avg (opt-out allowed), 11 h daily rest (reg 10), 20 min break over 6 h (reg 12)
Elevated risk
Driving 200-500 km a day between outreach clinics, lone home visits, manual-handling and equipment assessments, then late-night documentation
Long rural drives at dawn and dusk, multi-day circuits, early starts for remote clinics; day work
How the suite fits
How each product connects to your obligations
Grades describe how strongly a product connects to an obligation. None discharges an obligation, and none carries a compliance warranty.
Sleepfit
Supports your general duty of care
No UK rule names a sleep screen for allied health practice. Sleepfit supports your regulation 3 risk assessment under the Management of Health and Safety at Work Regulations 1999 where poor sleep is a foreseeable risk. It screens; diagnosis stays with your clinicians.
No UK rule names a pre-duty fitness check for allied health practice. Fatiguefit4Duty supports your general duty under s 2 of the Health and Safety at Work etc. Act 1974. A fitness-for-duty check, not a fitness-for-duty decision - the duty call stays with you.
Awareness eLearning supports the training you must give under s 2(2)(c) of the Health and Safety at Work etc. Act 1974 and regulation 13 of the 1999 Management Regulations with fatigue and sleep content. No UK rule names fatigue training for allied health practice.
RIDDOR 2013 requires you to report and record specified incidents in allied health practice but names no cause, and no fatigue review is required. Was It Fatigue? supports your own investigation. A structured judgement aid, not a determination of cause.
No UK rule reaches sleep in new-parent households in allied health practice. SleepWellBaby supports your working parents through the most disrupted period of their own sleep; it is offered as a wellbeing benefit, not a compliance step.
No UK rule names a fatigue tool, so this supports your HSWA 1974 s 2 duty and reg 3 risk assessment. Sleepfit screens your practitioners for sleep disorders; Fatiguefit4Duty adds a point-of-duty self-check. Prevention adds Awareness eLearning with a completion record.
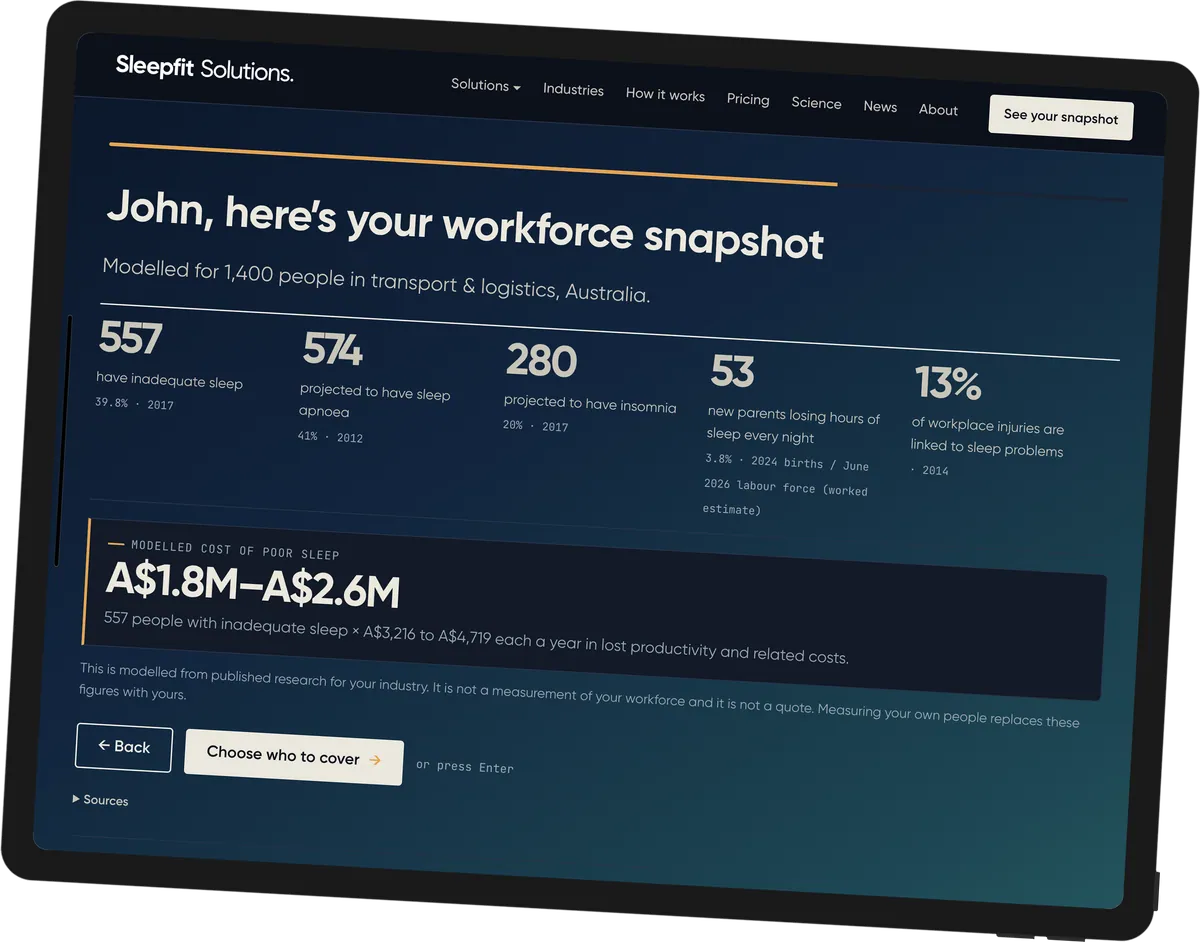
See what sleep and fatigue mean for your mental health & allied health workforce.
Tell us roughly how many people you employ. Your snapshot models how many are likely sleeping poorly and what it costs, from published research for mental health & allied health. Then choose who you’d cover, and we’ll take you to the right next step.