Sleep-health indicators and sleep improvement

Sleepfit

Measurement of the sleep your workforce is actually getting, with established sleep-health questionnaires that identify employees who may benefit from clinical evaluation, including people who would not otherwise present to a health service.

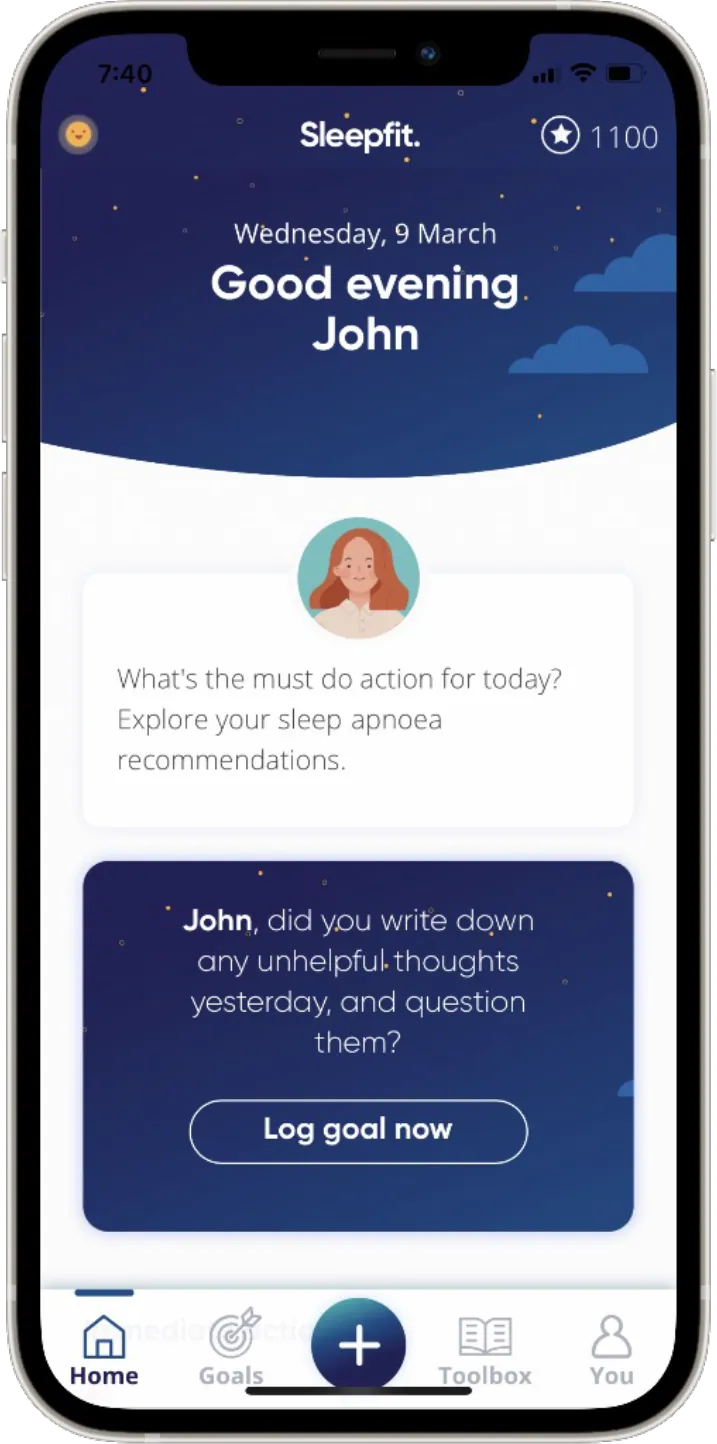
Sleepfit’s home screen: an evening greeting, today’s must-do action (explore your sleep apnoea recommendations) and a goal to log.

The problem

The sleep problems that matter most are the ones nobody reports

Sleep apnoea, insomnia and distress are common in shift-working populations and mostly undiagnosed. They do not show up in a roster or a health plan until something goes wrong.

Sleepfit measures sleep health at population scale, privately, identifies employees who may benefit from clinical evaluation, and gives each person a route to their own doctor.

Why do we sleep? Watch the video · 1:07

The size of the problem

National figures for the United Kingdom, from published research. They are modelled, not measured in your workforce.

  • 35%get less than 7 hours' sleep2013 (Understanding Society)
  • 17.8%projected to have moderate-to-severe sleep apnoea2024 (HSE 2019)
  • 29%projected to have insomnia2024 (UK Biobank 2006-2010)
  • £1,140lost productivity per affected employee each year
Sources
  1. Barnes M, Byron C, Beninger K. Sleep patterns and health: analysis of the Understanding Society dataset. NatCen Social Research, 2013.
  2. Kinoshita R, et al. Estimated prevalence of obstructive sleep apnea by occupation and industry in England. SLEEP Advances, 2024.
  3. de Lange MA, et al. Insomnia symptom prevalence in England: UK Biobank. BMJ Open, 2024.
  4. Rosekind MR, et al. The Cost of Poor Sleep: Workplace Productivity Loss and Associated Costs. Journal of Occupational and Environmental Medicine, 2010;52(1):91-98, applied to average earnings in the United Kingdom (ONS Average Weekly Earnings, whole economy, total pay, June 2026).

Stories

When a sleep disorder went unchecked

Published cases from the United Kingdom and the United States where sleep apnoea, insomnia or chronic short sleep sat behind a crash, a claim or lost work.

  • Oct 2016 · California, United States

    Truck driver with undiagnosed sleep apnea falls asleep in traffic stop; fatigued coach driver hits him, 13 killed

    • Safety

    Before dawn on an interstate highway, a truck driver failed to move off after a short police traffic break, most likely because he had fallen asleep, and a tour coach traveling at highway speed crashed into the back of the stopped truck, killing the coach driver and 12 passengers. The National Transportation Safety Board found the truck driver was at very high risk of obstructive sleep apnea and had never been tested, and that the coach driver failed to react because of fatigue after a disrupted sleep the previous day. It also faulted the road authority's traffic management plan for the traffic break.

    Case US-transport-10Report an issue
See all fatigue news

How it works

Sleep health, measured privately

Each employee completes a private, clinically structured sleep assessment on their own phone and gets a result, an action plan and, where a score is above a questionnaire’s cut-off, a letter they can choose to take to their own doctor. It works at the level of defence where most fatigue starts: whether people actually get the sleep their roster allows. The employer sees aggregate results only.

  1. Step 01

    Assessment

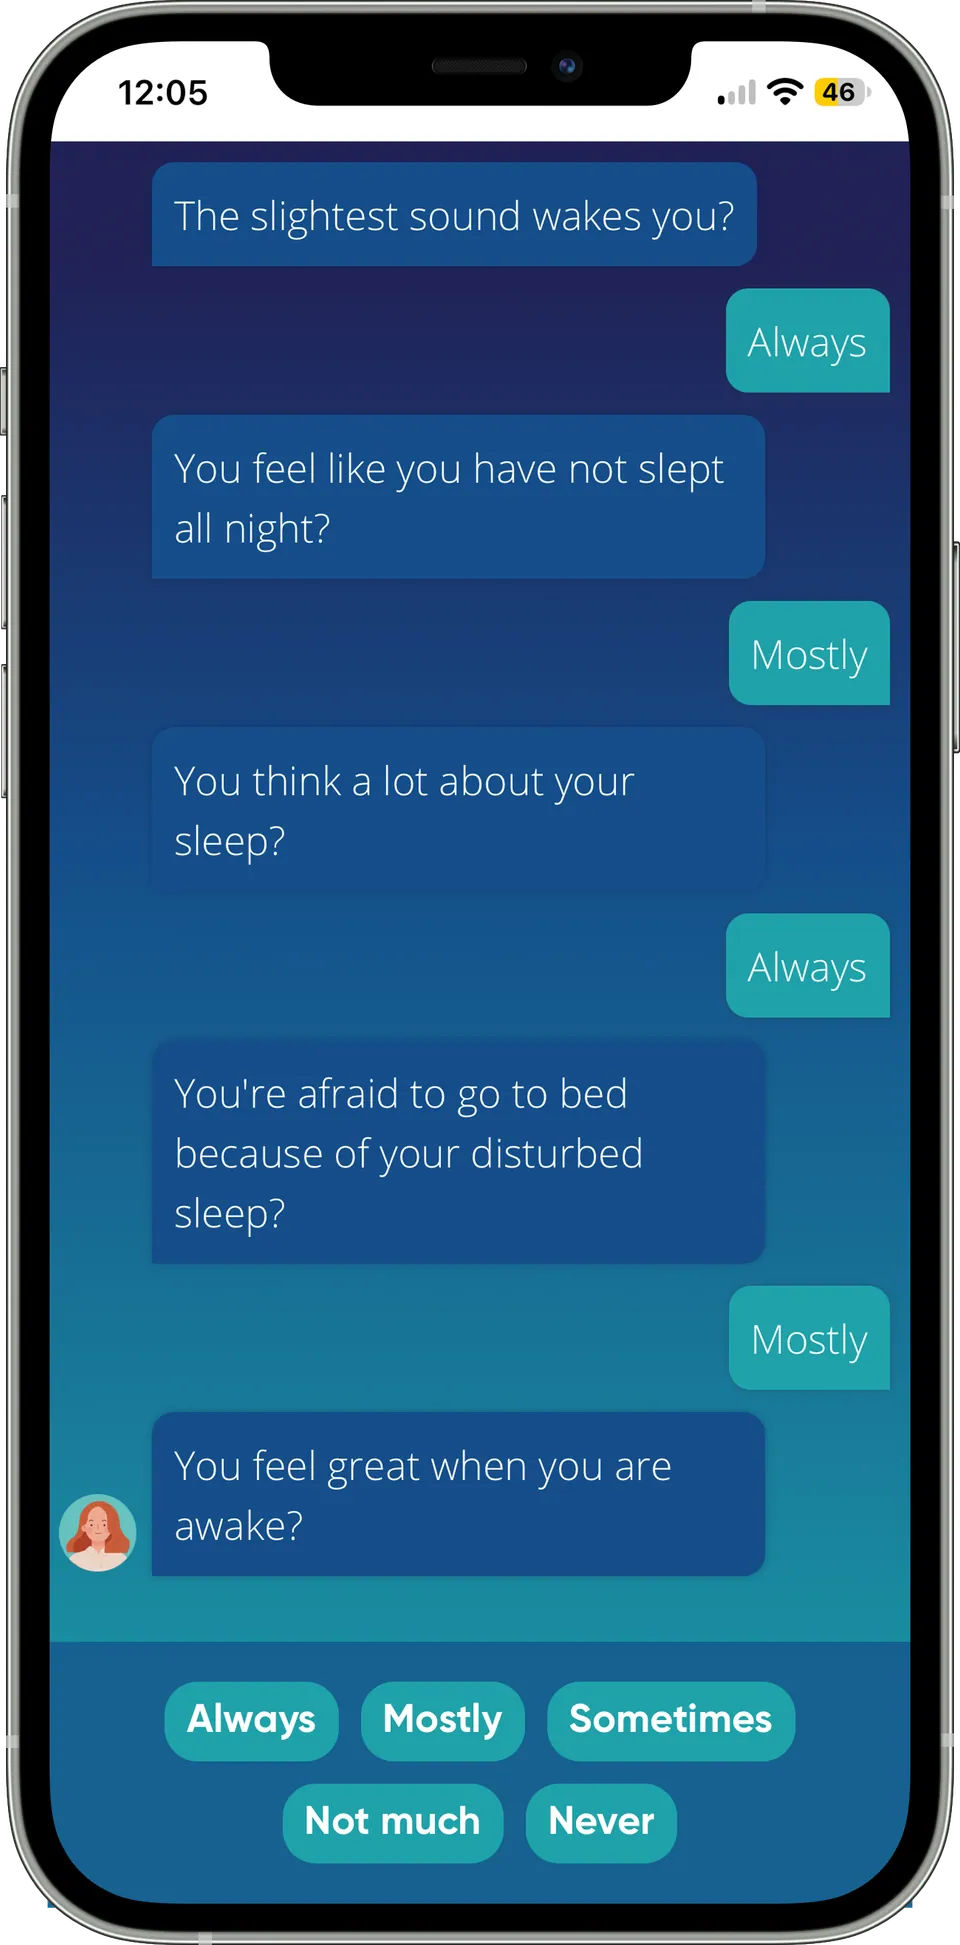
    A clinically structured sleep assessment on the employee’s own phone. Five published instruments, one sitting.

    The Sleepfit assessment as a conversation: questions such as whether the slightest sound wakes you, each answered from Always to Never.
  2. Step 02

    Result and action plan

    An individual result with an action plan generated from their own responses, not a generic library.

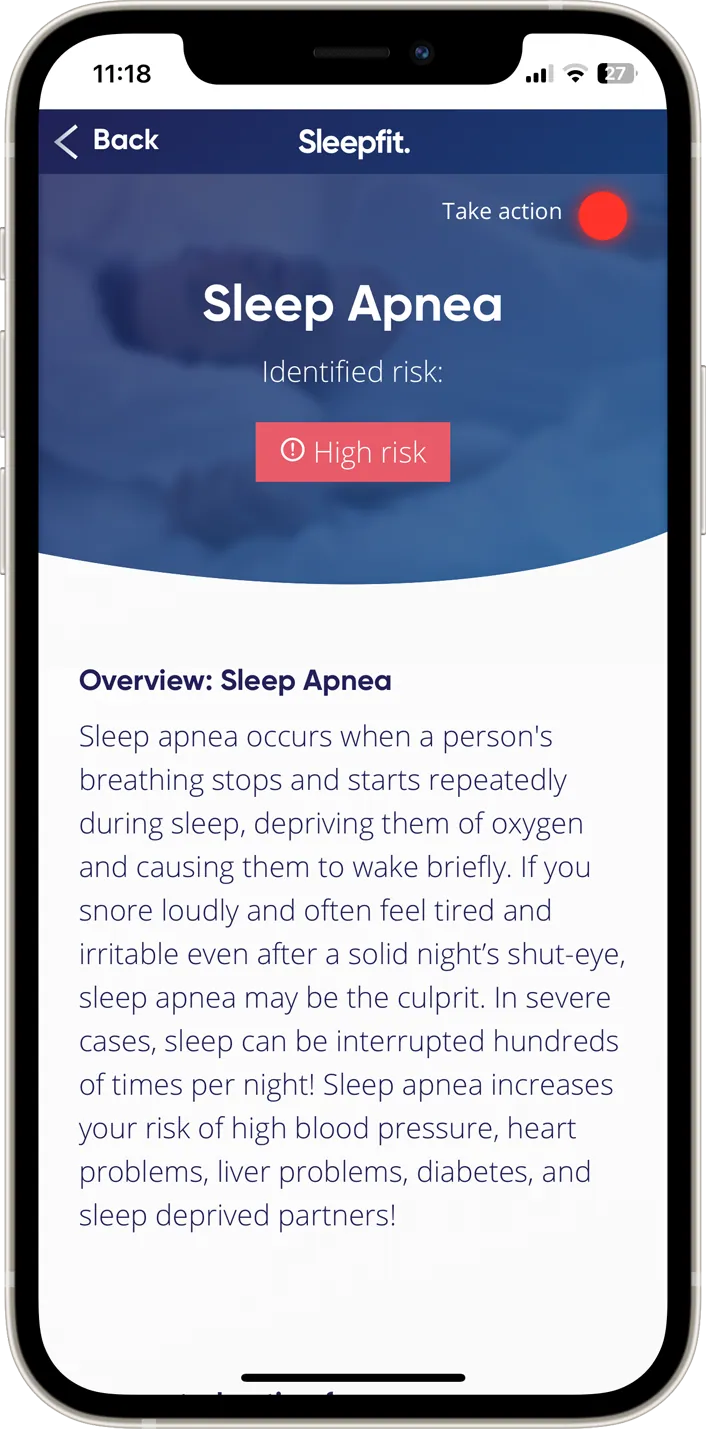
    A Sleepfit result: sleep apnoea identified at high risk, with an overview and a prompt to take action.
  3. Step 03

    A letter for their doctor

    Where a score is above a questionnaire’s cut-off, a consent-gated letter the employee can choose to download and take to their own doctor.

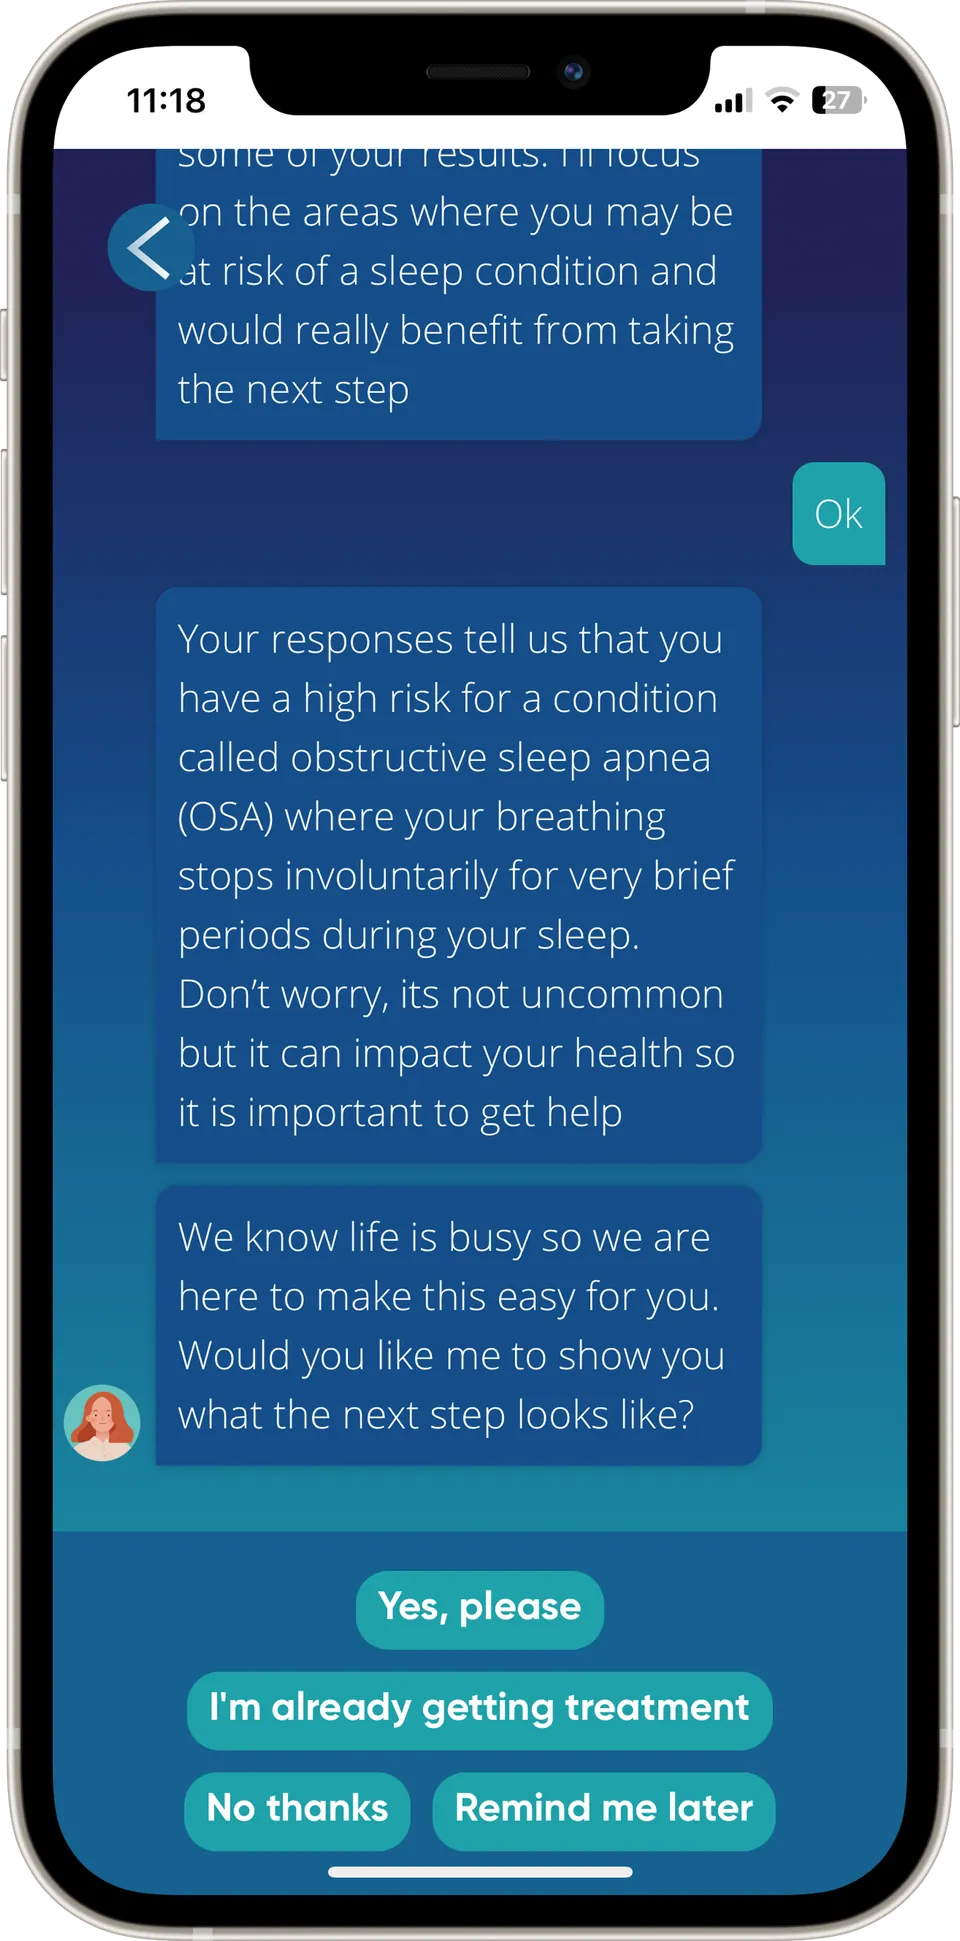
    Sleepfit’s guide explaining a high risk of obstructive sleep apnoea and offering to show the next step: yes please, already getting treatment, no thanks, or remind me later.
  4. Step 04

    Check-in and reassessment

    A three-item daily check-in (duration, quality, energy) feeding a sleep diary, and a reassessment at 14 days.

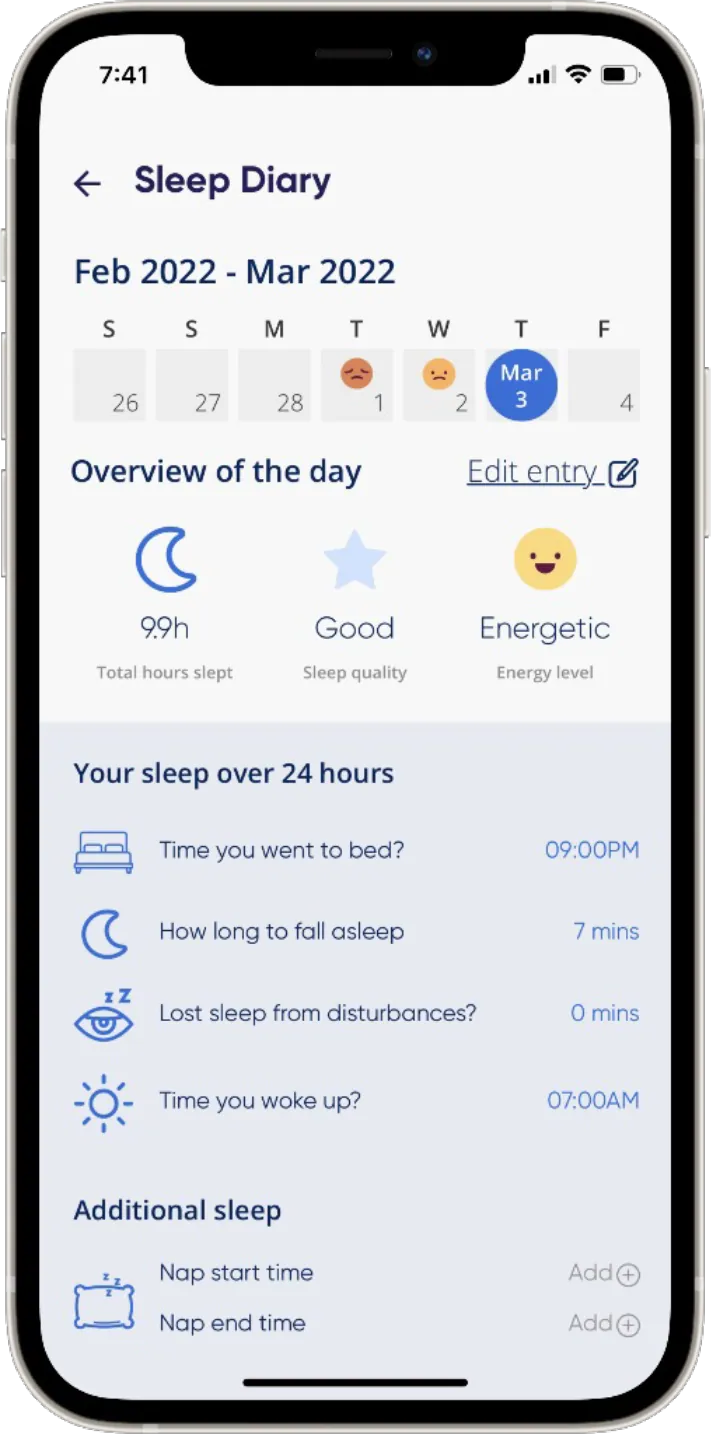
    The Sleepfit sleep diary: hours slept, sleep quality and energy for the day, and the night’s sleep over 24 hours.

Undiagnosed sleep apnoea changed my family. It’s treatable, and too often nobody asks. Sleepfit asks, privately, and gives each person a route to their own doctor, before it costs someone else’s family.

Daniel PlattCo-founder and CEO

Sleep is so often overlooked, yet it’s the foundation of good health. Many people with a sleep problem don’t know it, or don’t know it’s treatable. Sleepfit gives everyone a private, easy way to check their sleep health, and somewhere to go next.

Melissa WebsterFounder

Rollout

How we roll it out

  1. Scope

    Agree the cohort and how people will hear about it.

  2. Set up

    Access, your privacy notice and the minimum cell size for reporting.

  3. Launch

    People complete the assessment privately, on their own phone.

  4. Review

    Aggregate results after launch, and again after reassessment.

What the client sees

Who sees what

No individual result is reported to the employer. A minimum cell size applies to every aggregate figure so small teams cannot be re-identified. Any letter for the employee’s doctor is released only by the employee.

Priced on prevalence, not headcount. How pricing works.

  • The employee

    Everything, privately

    • Their result and action plan
    • A letter for their own doctor, released only by them
    • Their daily check-in and sleep diary
  • Their manager

    Nothing

    • Any result
  • The employer

    Aggregate results

    • Reporting by cohort and, where numbers permit, location and craft
    • A minimum cell size on every figure
    • Any individual result
    • Any letter for an employee’s doctor

Evidence

What we can show

Two independent studies from CQUniversity’s Appleton Institute found significant improvement in subjective sleep health and insomnia severity after using Sleepfit. Neither was powered to establish efficacy against a control group.

In a rail deployment, 62% of employees who scored above a questionnaire’s cut-off took action towards clinical follow-up.

What it does not establish

It identifies employees who may benefit from clinical evaluation. It does not diagnose any condition. Only a health professional can do that. A score above a questionnaire’s cut-off suggests a conversation with a health professional may be helpful; it is not a condition, and an above-cut-off rate is not a prevalence rate. It does not measure fatigue at the point of duty or make a fitness-for-duty determination.

In practice

Rail · Shift work

A rail operator offered Sleepfit to its shift-working workforce.

More than 1,000 employees completed a sleep assessment. A quarter came back for a second, a mean of 93 days later.

In partnership with

  • Research partner

    Independently studied Sleepfit with shift workers

    Researchers at CQUniversity’s Appleton Institute ran two independent, peer-reviewed studies of Sleepfit, with paramedics and with shift workers. They found significant improvement in subjective sleep health and insomnia severity; neither study was powered to establish efficacy against a control group.

FAQs

Questions we’re often asked

Does the employer see individual results?

No. No individual result is reported to the employer. Reporting is aggregate, with a minimum cell size so small teams can’t be re-identified, and any letter for the employee’s doctor is released only by the employee.

Does Sleepfit diagnose sleep disorders?

No. It does not diagnose any condition. Only a health professional can do that. Sleepfit identifies employees who may benefit from clinical evaluation, and the employee can choose to download a consent-gated letter to take to their own doctor.

What does the assessment use?

Five published instruments in one sitting, including STOP-Bang for sleep apnoea risk, the Regensburg Insomnia Scale and the PHQ-4.

What evidence is there that it helps?

Two independent studies from CQUniversity’s Appleton Institute found significant improvement in subjective sleep health and insomnia severity after using Sleepfit. Neither was powered to establish efficacy against a control group.

How is it priced?

On prevalence, not headcount: your whole cohort gets access, and you pay for the share predicted to need it.

Can someone delete their account and data?

Yes, at any time, in the app or by request. All personal data associated with the account is removed, and deletion can’t be undone.

Pathways

Where to go next

See how Sleepfit fits the regulation in your industry, and what else we would start with there.

All 33 industries

Other solutions interconnected with Sleepfit

Interested in Sleepfit for your organisation?

Tell us a little about your organisation and which solutions you’re looking at, and our team will be in touch.

Sleepfit’s home screen: an evening greeting, today’s must-do action (explore your sleep apnoea recommendations) and a goal to log.