Aged Care & Disability Services · United States

Aged and disability care depends on carers who sleep well.

Carers and nurses work nights, sleepovers and rotating shifts, often across two jobs. Fatigue raises the risk of medication errors, falls and manual-handling injury with vulnerable people.

Regulation changed Dec 3, 2025

Aged Care & Disability Services workforce

Who this page covers

  • Disability supported accommodation
  • Home care and community aged care
  • NDIS in-home support workers
  • Out-of-home care and residential youth care
  • Residential aged care

Reg Watch

What’s changed, and what’s coming

Regulatory change that affects how you manage fatigue in aged care & disability services: what has changed in the last 12 months, and what is on the way.

Recent changeFrom December 3, 2025

Specific to aged care & disability services

An interim final rule published 3 December 2025 repealed the 2024 federal minimum staffing standards for nursing homes. The sufficient-staffing duty in 42 CFR 483.35 and state staffing laws still apply.

Read the change

Regulatory changes checked as at October 1, 2026.

Regulation

Who regulates it, and what they expect

No federal rule limits how long a US nursing home worker may be on duty. The CMS minimum staffing standards - 3.48 total nurse hours per resident day and a registered nurse on site around the clock - were vacated by two federal courts, blocked by statute until 30 September 2034, and repealed by CMS with effect from 2 February 2026. What 42 CFR 483.35 requires today is sufficient staff on a 24-hour basis, a registered nurse for at least 8 consecutive hours a day 7 days a week, and a full-time director of nursing. Fatigue is not mentioned anywhere in it.

Regulated by
  • Centers for Medicare & Medicaid ServicesCMS

Logos identify the regulator and don’t imply endorsement.

Who regulates it

State governments (through nurse mandatory-overtime laws in sixteen states) and the federal Centers for Medicare & Medicaid Services (CMS, for facilities billing Medicare or Medicaid) are the relevant sector-specific regulators. The general US workplace-safety baseline - OSHA, the ADA, and the FMLA - applies underneath all of this.

Your obligations

Staff sufficiently on a 24-hour basis, provide registered nurse services for at least 8 consecutive hours a day 7 days a week, and designate a registered nurse as full-time director of nursing, each subject to waiver. Your facility assessment under 42 CFR 483.71 must consider staffing needs unit by unit and shift by shift, with direct care staff involved in making it. Your QAPI program must track adverse resident events and analyze their causes. In Pennsylvania, Act 102 bars mandating a nurse aide beyond their scheduled shift.

Consequences

CMS survey deficiencies attach to staffing, not to hours. Insufficient staffing under 42 CFR 483.35 can be cited up to immediate jeopardy and, at the extreme, CMS can terminate the Medicare and Medicaid provider agreement, which ends the facility's revenue. OSHA reaches fatigue only through the General Duty Clause, and only where the hazard is recognized. In Pennsylvania and Maine a state labor department can fine you for mandating overtime. Workers' compensation covers the injured worker either way.

Penalties

OSHA maximums are at 2025 levels and in force for 2026: $16,550 serious or other-than-serious, $165,514 willful or repeat, $16,550 per day failure to abate. Pennsylvania Act 102 fines run $100 to $1,000 per violation. New York Labor Law 167 penalties are up to $1,000, $2,000 and $3,000 for a first, second and third violation within 12 months. There is no federal fatigue penalty.

Sources: 42 CFR 483.35 nursing services; CMS interim final rule repealing the 2024 minimum staffing rule (December 2025); Pennsylvania Act 102 of 2008; NY Labor Law s167; OSHA General Duty Clause and 2026 penalty schedule; Americans with Disabilities Act; Family and Medical Leave Act.

Fatigue-critical roles

Where fatigue matters most in aged care & disability services

The roles where a fatigued worker is most likely to cause serious harm, the tasks that carry the risk, and why fatigue builds up in them.

RoleRiskHigh-risk tasksWhy fatigue builds
Certified nursing assistant (CNA) / state-tested nurse aide (STNA)
Rules
Regulatory designation
Nurse aide in a certified facility (42 CFR 483.35(d) training and competency); otherwise general duty
Hours and rest
None federal; 42 CFR 483.35 requires sufficient staffing, not hours limits
High riskNight rounds alone or in pairs: hoist and two-person transfers, falls response, medication assistance, continence care and repositioning across a whole wingPermanent or rotating nights, sleepover or sleep-in shifts, 10-12 h shifts, multiple employers, 06:00-07:00 starts
Charge nurse (RN or LPN), skilled nursing / long-term care facility
Rules
Regulatory designation
Licensed nurse under 42 CFR 483.35(b): licensed nurse 24 h a day; RN 8 consecutive h a day, 7 days a week
Hours and rest
None federal; some state overtime limits
High riskSole RN overnight: medication rounds and controlled-drug checks, recognizing deterioration and deciding on hospital transfer, falls assessment, supervising carersRotating nights as the only RN on site, 10-12 h shifts, agency fill and double shifts to keep 24/7 RN cover
Home health aide (HHA) / personal care aide (PCA)
Rules
Regulatory designation
Home health aide in a Medicare-certified agency (42 CFR 484.80 training and competency); otherwise general duty
Hours and rest
None federal (FLSA overtime pay applies to most home care workers since 2015)
High riskDriving own car between 8-12 client homes a day, lone personal care and transfers without a second carer, medication prompting; early and late callsSplit or broken shifts 07:00-21:00 with unpaid gaps, tight travel windows, lone work, weekend runs, multiple employers
Direct support professional (DSP) - group home / ICF/IID
Rules
Regulatory designation
Direct care staff in an ICF/IID (42 CFR 483.430) or HCBS waiver setting; otherwise general duty
Hours and rest
No federal hours cap for adults; FLSA prices overtime only
High riskActive nights in group homes: responding to behaviors of concern, applying authorized restrictive practices, seizure response, manual handling, driving residentsActive and sleepover nights, 24 h shifts in some services, short-staffed lone nights, rotating rosters

Stories

When fatigue made the record

Published findings and prosecutions from regulators, courts and investigators in the United States.

  • Oct 2024 · Texas, United States

    Care facility pays $80,000 after firing night nurse with sleep disorder who asked to keep to agreed shifts

    • Legal
    • Financial

    A rehabilitation and assisted living facility hired a night-shift nurse with a sleep disorder for three 12-hour shifts a week, then told her she must also work a fourth 12-hour shift every other week. When she asked, as a disability accommodation, to keep to the hours in the job posting, she was demoted and then dismissed. The Equal Employment Opportunity Commission sued under the Americans with Disabilities Act and the facility settled for $80,000 under a three-year consent decree.

    Case US-agedcare-01Report an issue

See all aged care & disability services news

How the suite fits

How each product connects to your obligations

Grades describe how strongly a product connects to an obligation. None discharges an obligation, and none carries a compliance warranty.

Sleepfit

Supports your general duty of care

Screens your direct care workforce for sleep apnea, insomnia and distress risk. No CMS requirement names screening, so this supports a recognized-hazard case, not a compliance step.

About Sleepfit

Fatiguefit4Duty

Supports your general duty of care

Checks fitness before medication rounds, transfers and lone overnight shifts. Neither CMS nor OSHA requires a fitness check in long-term care, so this supports a general duty argument.

About Fatiguefit4Duty

Awareness eLearning

Supports your general duty of care

Builds fatigue literacy across a rotating roster. Nurse aide training content at 42 CFR 483.152 does not include fatigue, so this adds coverage the federal rule does not ask you for.

About Awareness eLearning

Was It Fatigue?

Supports your general duty of care

42 CFR 483.75 requires you to track adverse resident events and analyze their causes, and it does not name fatigue. Was It Fatigue? supports that analysis by testing whether fatigue played a part. A structured judgment aid, not a determination of cause.

About Was It Fatigue?

SleepWellBaby

Supports staff whose sleep is broken by an infant at home. No US aged care regulation touches worker sleep, so this is a voluntary retention and wellbeing measure with no hook engaged.

About SleepWellBaby

Recommended bundle

Where we’d start in aged care & disability services

Every bundle is priced on prevalence: your whole cohort gets access, and you pay for the share predicted to need each product. How pricing works.

Recommended · Levels 2 and 3

Shift Worker Bundle

Sleep screening and a point-of-duty check for the workers who need it most.

Why this pairing in the United States

No CMS rule names a fatigue tool, so this supports your General Duty Clause case under s 5(a)(1). Sleepfit screens your direct care staff for sleep disorders, confidentially; Fatiguefit4Duty adds a point-of-duty self-check. Prevention adds Awareness eLearning with a completion record.

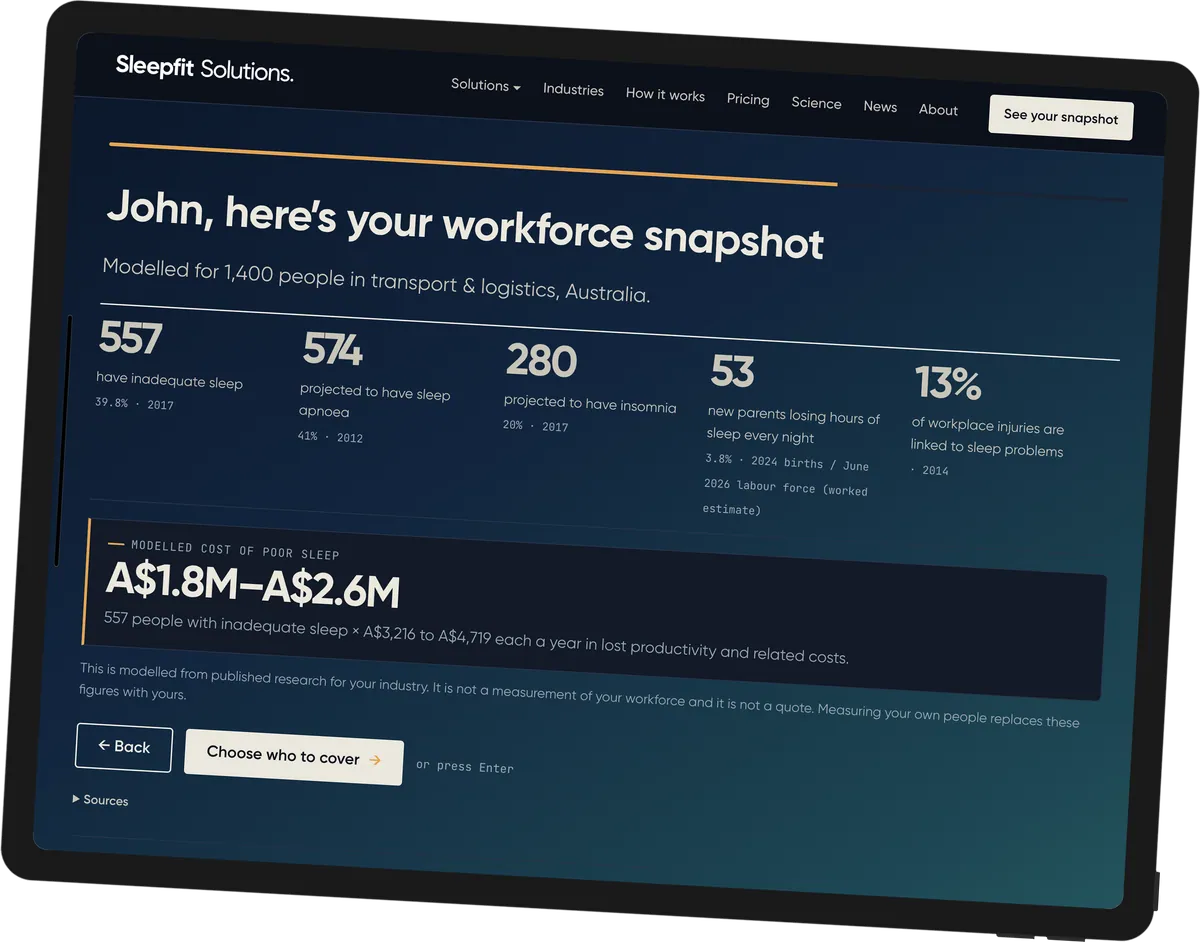
See what sleep and fatigue mean for your aged care & disability services workforce.

Tell us roughly how many people you employ. Your snapshot models how many are likely sleeping poorly and what it costs, from published research for aged care & disability services. Then choose who you’d cover, and we’ll take you to the right next step.

A sample workforce snapshot on a tablet: modeled sleep problems and the cost of poor sleep for 1,400 people in transport and logistics.