Soins de santé et soins infirmiers · Canada

Le sommeil et la fatigue : soins de santé et soins infirmiers

Nurses and doctors work rotating 24/7 rosters, nights and extended shifts. Fatigue impairs attention and judgment, putting medication safety, clinical decisions and the drive home at risk.

Réglementation modifiée : 1 juin 2026

Main-d’œuvre du secteur Soins de santé et soins infirmiers

Ce que couvre cette page

  • After-hours GP and home-visit doctors
  • Doctors in training (residents)
  • Forensic mental health hospitals (voir aussi Services correctionnels et de détention)
  • Hospital pathology and imaging
  • Nursing agencies and locum pools (voir aussi Services professionnels)
  • Private hospitals
  • Psychiatric hospitals and inpatient mental health
  • Public hospitals

Veille réglementaire

Ce qui a changé, et ce qui s’en vient

Les changements réglementaires qui touchent votre gestion de la fatigue en soins de santé et soins infirmiers : ce qui a changé au cours des 12 derniers mois, et ce qui s’en vient.

Les détails réglementaires et les données de recherche de cette page sont présentés en anglais.

Changement récentDepuis le 1 juin 2026

Propre au secteur soins de santé et soins infirmiers

Manitoba passed laws on 1 June 2026 to set nurse-to-patient ratios and benchmarks to eliminate mandatory nurse overtime by regulation. Neither is in force until proclaimed.

Voir le changement

Changement à venirAucune date fixée

Manitoba's nurse ratio and mandatory overtime laws (assented 1 June 2026) start on a day fixed by proclamation, with ratios, benchmarks and compliance plans to follow by regulation. Quebec employers have until 6 October 2026 to have a prevention program addressing psychosocial risks.

Changements réglementaires vérifiés au 1 octobre 2026.

Réglementation

Qui la réglemente, et ce qui est attendu

Les détails réglementaires et les données de recherche de cette page sont présentés en anglais.

Nurse staffing and doctors' hours are set province by province, almost entirely by collective agreement rather than statute. British Columbia has phased in minimum nurse-to-patient ratios since January 2025 - 1:1 in intensive care, 1:4 on medical and surgical units - as a term of the provincial nurses' agreement, not as law. Manitoba has passed ratio and mandatory-overtime legislation that awaits proclamation. Ontario physicians, residents included, are excluded from Employment Standards Act hours and rest limits, so a resident's call ceiling rests on the PARO-OTH agreement alone.

Qui la réglemente

No province has a nurse-to-patient ratio in force by statute. British Columbia has phased in minimum ratios since January 2025 under the province-wide nurses' collective agreement, and Manitoba has passed ratio and mandatory-overtime laws awaiting proclamation. Resident doctors' hours come from housestaff agreements. Oversight sits with provincial labor ministries, workers' compensation boards and human rights tribunals.

Vos obligations

Hospitals owe nurses, allied health and support staff the general duty to take every reasonable precaution for their safety, plus their province's employment standards on hours and rest. No province yet requires a nurse-to-patient ratio by law: in British Columbia the ratios bind as a term of the provincial nurses' collective agreement; in Ontario it is hospital policy and bargaining. Resident physicians are the exception - Ontario's Employment Standards Act gives physicians no hours-of-work or rest-period entitlement, so their only limits are contractual. You must also accommodate a diagnosed sleep disorder to undue hardship.

Conséquences

With no ratio statute and no legal cap on shift length, exposure runs three ways. A prosecution under your province's health and safety act if a fatigue-related incident shows the hospital was not managing fatigue as a foreseeable hazard under the general duty to take every reasonable precaution. A human rights complaint where a diagnosed sleep disorder was not accommodated to the point of undue hardship. And, most often of all, grievance and arbitration: where ratios, call frequency, maximum call length or post-call relief are collective agreement terms, an arbitrator can order a hospital to change its rosters and make affected staff whole. Arbitration is private, but the orders bind and awards are published.

Sanctions

Penalties come from provincial health and safety law, not from any staffing or duty-hour statute. Ontario's maximums, current in 2026, are $2,000,000 for a corporation, $1,500,000 for a director or officer and $500,000 for any other individual, the last two carrying up to 12 months' imprisonment. A corporation convicted of a second offence causing death or serious injury within two years faces a minimum fine of $500,000. Every other province sets its own maximums.

Sources: BC Nurses' Union on minimum nurse-to-patient ratios; Manitoba Bills 26 and 28; Ontario Bill 19, Patient-to-Nurse Ratios for Hospitals Act; Ontario ESA exemptions for health professions; PARO-OTH agreement; Canadian Family Physician (2025) on resident call shifts.

Postes critiques

Là où la fatigue compte le plus en soins de santé et soins infirmiers

Les postes où un travailleur fatigué risque le plus de causer un préjudice grave, les tâches qui portent ce risque, et pourquoi la fatigue s’y accumule.

Les détails réglementaires et les données de recherche de cette page sont présentés en anglais.

PosteRisqueTâches à risque élevéPourquoi la fatigue s’accumule
Resident physician (PGY-1+; 'resident' / 'résident' in Québec)
Règles
Désignation réglementaire
None specific - general duty; Ont. physicians exempt from ESA hours rules (O. Reg. 285/01); resident limits contractual (PARO-OTH, FMRQ)
Heures et repos
No statutory cap. PARO-OTH (Ont.): up to 24 h in-hospital call plus handover, max 7 in-house call nights in 28; Québec: 16 h maximum continuous duty (2011 arbitration award)
Risque critiquePrescribing and dosing, procedures and admitting unwell patients alone overnight; handover after a night shift or 24 h on-call; driving home afterwardsRotating nights, 12-14 h long days, 24 h on-call in some systems, quick returns; 60-80 h weeks in training posts
Registered nurse (RN); registered practical nurse (RPN, Ont.) / licensed practical nurse (LPN)
Règles
Désignation réglementaire
None specific - general duty; BC minimum nurse-patient ratios are collective-agreement terms (NBA), not statute
Heures et repos
Provincial ESA rest rules (Ont.: 11 h daily rest, 8 h between shifts) unless varied by collective agreement (e.g. ONA hospital CA)
Risque critiqueHigh-alert medicines (insulin, opioids, IV infusions) and double-checks at 03:00-05:00; observing deteriorating patients; patient handling; driving home after nights12 h day/night rotations or rotating 8/10 h shifts, quick returns, mandatory or voluntary overtime, consecutive nights
Staff physician / attending (anesthesiologist, surgeon, obstetrician)
Règles
Désignation réglementaire
None specific - general duty; most physicians hold hospital privileges as independent contractors, not employees
Heures et repos
None - Ont. O. Reg. 285/01 exempts physicians from ESA hours rules
Risque critiqueEmergency surgery, anaesthesia and obstetric delivery at night after a full day list; next-day elective list after being called in; driving in at 03:00Non-resident on-call 1:3 to 1:8, called in overnight, then a full day list next day; no rest rule after call-ins in most systems
Personal support worker (PSW, Ont.) / health care aide (Alta., Man.) / patient care aide
Règles
Désignation réglementaire
None specific - general duty (provincial OHS Act, e.g. Ont. OHSA s 25(2)(h); CLC s 124 if federal)
Heures et repos
Provincial ESA, e.g. Ont. ESA: 11 h daily rest, 8 h between shifts, 48 h/wk unless agreed
Risque élevéTwo-person patient transfers and repositioning, overnight falls watch and 1:1 observation ('specialling'), vital-sign rounds and escalation, mobilising patientsRotating or permanent nights, 12 h shifts, bank/agency shifts stacked on a primary job, 07:00 handovers
Hospital pharmacist (staff pharmacist)
Règles
Désignation réglementaire
None specific - general duty (provincial OHS Act, e.g. Ont. OHSA s 25(2)(h); CLC s 124 if federal)
Heures et repos
Provincial ESA, e.g. Ont. ESA: 11 h daily rest, 8 h between shifts, 48 h/wk unless agreed
Risque élevéVerifying and dispensing high-alert and paediatric doses overnight, aseptic compounding checks (chemotherapy, TPN), phone advice to wards while alone on-callResident nights in large hospitals or remote on-call after a day shift; lone overnight verification with no second checker
Medical laboratory technologist (MLT) / medical radiation technologist (MRT)
Règles
Désignation réglementaire
None specific - general duty (provincial OHS Act, e.g. Ont. OHSA s 25(2)(h); CLC s 124 if federal)
Heures et repos
Provincial ESA, e.g. Ont. ESA: 11 h daily rest, 8 h between shifts, 48 h/wk unless agreed
Risque élevéCross-matching and issuing blood, phoning critical results, CT and X-ray imaging and contrast checks overnight; lone on-call after a day shiftSingle-handed nights or call-ins after a full day, 24 h weekend on-call, broken sleep between call-ins

Cas

Quand la fatigue a laissé une trace

Constatations et poursuites publiées par les organismes de réglementation, les tribunaux et les enquêteurs (Canada).

Les détails réglementaires et les données de recherche de cette page sont présentés en anglais.

  • 2023 · Quebec, Canada

    Arbitrator rules nurse ordered to work 31 hours in 39 was subjected to abuse of management rights

    • Juridique

    A nurse in a regional Quebec public health service was ordered to work three consecutive shifts totalling more than 31 hours within a 39-hour period, and when she raised fatigue and said she could not continue, her manager threatened to call the police. The arbitrator found the practice went well beyond the limits generally accepted by the courts, that the employer had abused its management rights and created unreasonable working conditions, and ordered it to end all similar practices. The ruling reinforced earlier tribunal guidance that mandatory overtime should be used only in urgent and exceptional situations.

    Cas CA-healthcare-02Signaler une erreur

Voir toutes les actualités : soins de santé et soins infirmiers

Comment la suite s’inscrit

Comment chaque produit se rattache à vos obligations

Les cotes décrivent dans quelle mesure un produit se rattache à une obligation. Aucun ne vous acquitte d’une obligation, et aucun ne comporte de garantie de conformité.

Les détails réglementaires et les données de recherche de cette page sont présentés en anglais.

Sleepfit

Soutient votre devoir général de diligence

No Canadian healthcare rule requires a sleep health screen for clinical staff; resident duty hours come from collective agreements and accreditation, not statute. Sleepfit supports your general duty under provincial OHS law. It screens; diagnosis stays with your clinicians.

À propos de Sleepfit

Fatiguefit4Duty

Soutient votre devoir général de diligence

No Canadian healthcare rule names a point-of-duty fatigue check for nurses or physicians. Fatiguefit4Duty supports your general duty under provincial OHS law. A fitness-for-duty check, not a fitness-for-duty decision - the duty call stays with you.

À propos de Fatiguefit4Duty

Awareness eLearning

Soutient votre devoir général de diligence

No Canadian statute requires fatigue training for healthcare workers; your general OHS training duty applies, and any resident training expectations sit in accreditation. Awareness eLearning supplies fatigue and sleep content with a record.

À propos de Awareness eLearning

Was It Fatigue?

Soutient votre devoir général de diligence

Your OHS duty to investigate workplace incidents, and patient safety incident reviews, do not name fatigue under Canadian law. Was It Fatigue? supports a structured look at staff sleep and shift history. A structured judgment aid, not a determination of cause.

À propos de Was It Fatigue?

SleepWellBaby

No Canadian healthcare rule reaches sleep in new-parent households. SleepWellBaby is offered as a benefit to parents among your nurses, physicians and support staff, not as a compliance step.

À propos de SleepWellBaby

Forfait recommandé

Par où nous commencerions en soins de santé et soins infirmiers

Chaque forfait est tarifé selon la prévalence : toute votre cohorte y a accès, et vous payez pour la proportion qui devrait avoir besoin de chaque produit. Comment fonctionne la tarification.

Pourquoi ce choix (Canada)

No Canadian healthcare rule names a fatigue tool; resident hours sit in agreements, so your provincial OHS Act applies. Sleepfit screens clinical staff, Fatiguefit4Duty adds a point-of-duty check and Awareness eLearning trains with a record. Fatigue Lifecycle adds incident review.

Ce que le sommeil et la fatigue représentent pour votre effectif en soins de santé et soins infirmiers.

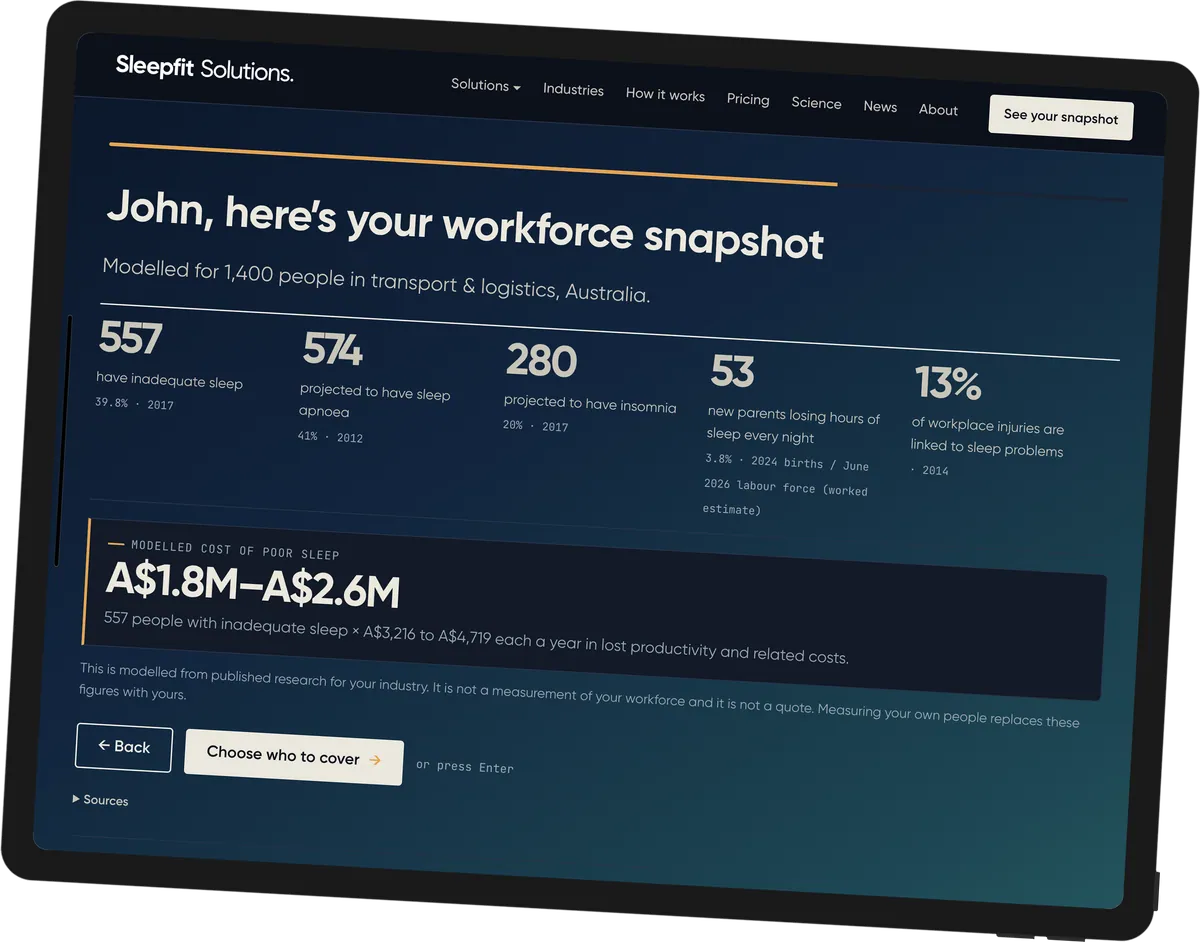
Indiquez-nous environ combien de personnes vous employez. Votre portrait estime combien dorment probablement mal et ce que cela coûte, à partir de la recherche publiée pour le secteur soins de santé et soins infirmiers. Choisissez ensuite qui couvrir, et nous vous mènerons à la bonne étape suivante.

Un exemple d’aperçu de la main-d’œuvre sur une tablette : troubles du sommeil modélisés et coût du mauvais sommeil pour 1 400 personnes dans le transport et la logistique.